What is plantar fasciitis?
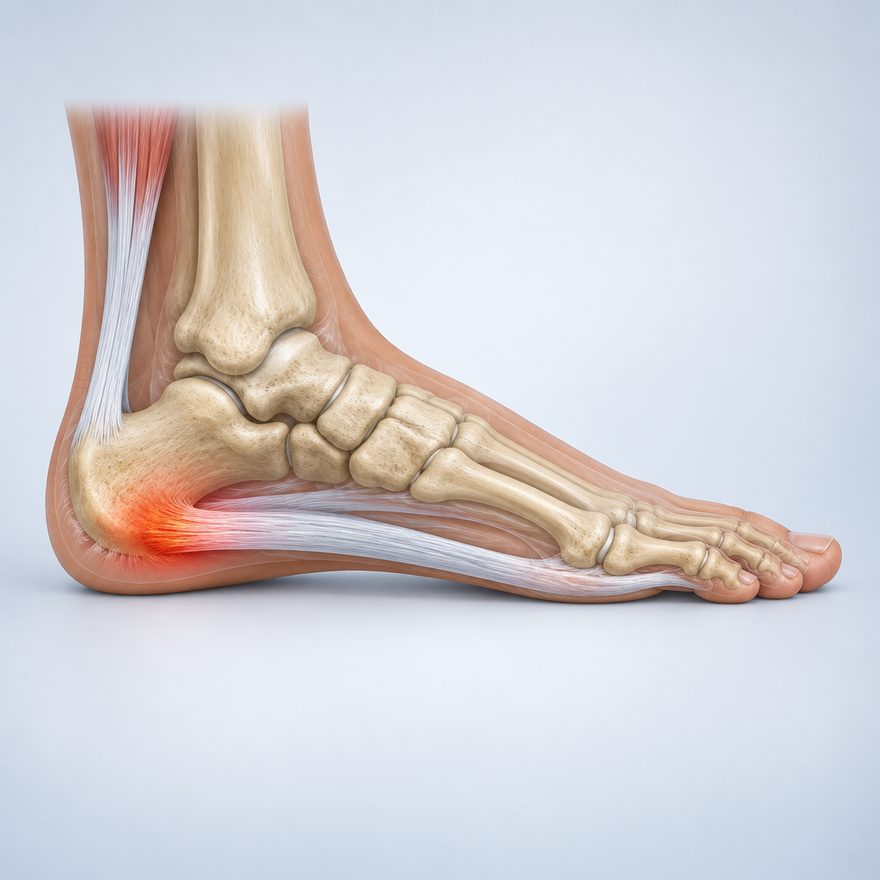
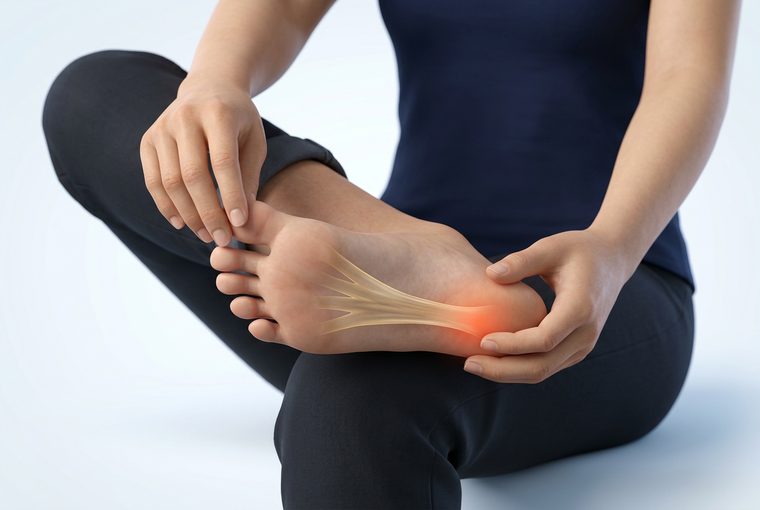
The plantar fascia is a thick, strong band of tissue that runs along the sole of the foot, from the heel bone to the base of the toes. It supports the arch and acts like a spring when you walk and run.
Plantar fasciitis develops when this band is overloaded, most often where it attaches to the underside of the heel bone. Repeated strain causes small areas of damage and thickening that the tissue struggles to repair. Despite the name, inflammation is usually not the main problem, which is why rest alone often doesn't fix it.
Plantar fasciitis symptoms
Pain usually builds up gradually over weeks or months, rather than starting with a single injury.
Common symptoms
- Sharp or stabbing pain under the heel, usually towards the inside
- Pain with the first steps in the morning, or when standing up after sitting, which eases after a few minutes of walking
- Pain after long periods of standing or walking, rather than during exercise itself
- Tenderness when you press on the underside of the heel
- Stiffness or aching along the arch of the foot
How it progresses
It usually progresses in these stages:
- EarlyPain mainly with the first steps in the morning, easing quickly once you start moving.
- MiddlePain also comes on after standing or walking for a while, and at the end of the day.
- LateThe heel hurts for much of the day, and you may start limping or changing how you walk.
Symptoms don't always follow this order. Many cases settle within a year, though some take longer, and the pain can come back.
Causes and risk factors
Plantar fasciitis usually develops when the plantar fascia takes more load than it is used to, often over weeks or months.
- Long hours standing or walking on hard floors, such as in retail, catering, security or teaching
- A sudden increase in walking, running or training, or starting a new sport
- Tight calf muscles or a stiff ankle
- Footwear with little support or cushioning, such as flat shoes, worn-out trainers or flip-flops
- Being overweight, or recent weight gain
- Flat feet or high arches
It is most common in people aged 40 to 60, and in runners.
Self-checks
These two simple checks can give a first indication, but they cannot confirm a diagnosis. Stop if either check causes sharp pain.
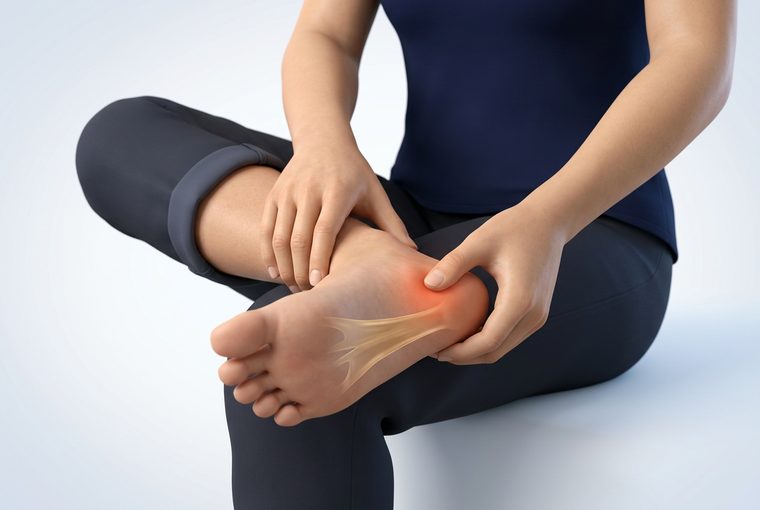
A positive result does not mean you have plantar fasciitis, and a negative one doesn't rule it out. If heel pain keeps coming back, or affects your work or walking, have it properly assessed by a healthcare professional.
Heel pain isn't always plantar fasciitis
Heel pain has several possible causes. Finding where the pain is coming from is the key to choosing the right treatment.
Plantar fasciitis (the band under the heel)
- Where it usually hurts
- Under the heel, usually towards the inside; can spread along the arch
- Other clues
- Worst with the first steps in the morning or after rest
Achilles tendinopathy (the tendon at the back of the heel)
- Where it usually hurts
- The back of the heel, or the tendon just above it
- Other clues
- Stiff in the morning; pain when pushing off, climbing stairs or running
A trapped nerve (in the foot, or from the lower back)
- Where it usually hurts
- The inside of the heel and the sole, or pain spreading down from the lower back
- Other clues
- Burning, numbness or tingling; may be worse at night or after long standing
Heel bone stress fracture
- Where it usually hurts
- The whole heel, including the sides of the heel bone
- Other clues
- Pain that builds with weight-bearing activity such as running; pain when squeezing the sides of the heel; more likely after a sudden increase in training
Back problems and heel pain can also occur together: a trapped nerve in the lower back (sciatica) can cause pain or numbness in the heel. That is why Dr. Ho checks the lower back, hips, knees and feet together.
Further reading: Sciatica, Lower back pain.
How it is diagnosed
Diagnosis relies mainly on your history and a physical examination. Scans are usually not needed.
Your history: When and where the pain appears, your work and footwear, and any recent changes in activity.
Physical examination: Pressing on the heel and arch, checking calf flexibility and ankle movement, and watching how you stand and walk. The lower back, hips and knees are also checked to rule out other causes.
Further tests: If the diagnosis is unclear, or pain doesn't improve with treatment, Dr. Ho may suggest imaging such as ultrasound or an X-ray, refer you for a nerve conduction study if a nerve may be involved, or refer you to an orthopaedic doctor.
Plantar fasciitis treatment options
Most people improve with non-surgical treatment. Treatment usually aims to settle the pain first, then gradually build up how much load the foot can take; surgery is rarely needed.
Non-surgical treatment
Managing the load: Cutting back on long periods of standing and high-impact activity for a while, rather than stopping all walking, then building back up gradually.
Stretching and strengthening exercises: Calf and plantar fascia stretches, and exercises that strengthen the foot and calf. Stretching is widely recommended as a first step.
Supportive footwear and insoles: Shoes with good arch support and cushioning, with insoles or custom orthotics, may help ease the load on the heel.
Hands-on and soft tissue treatment: Releasing tight tissues in the calf and the sole of the foot, and mobilising the ankle and foot joints, which may help ease pain in the short term.
Shockwave therapy: Some studies suggest shockwave therapy may help heel pain that has lasted several months, although results vary.
Ultrasound therapy: The research evidence is limited; it is generally used only as a supporting treatment.
Treatment prescribed by a doctor
Medication or injections: Painkillers or anti-inflammatory medication may ease pain in the short term. A steroid injection may ease pain for a few weeks, but the effect is often short-lived, and repeated injections carry a small risk of weakening or tearing the plantar fascia and thinning the heel pad, so it is not usually the first choice.
Surgery
Plantar fascia release: Part of the plantar fascia is cut to release tension, through open or keyhole surgery. Surgery is generally considered only for severe pain that persists after 6 to 12 months of non-surgical treatment.

Prevention and self-care
Small changes to how you stand, walk and stretch can help reduce the load on the heel, at work and at home.
- Stretch your calves and the soles of your feet every day, especially before getting out of bed and after long periods of sitting.
- Wear supportive, cushioned shoes at home as well as outside; avoid going barefoot or wearing flat slippers on hard floors.
- Replace worn-out running shoes, and build up walking or running distances gradually.
- If you stand for long hours at work, use cushioned insoles or an anti-fatigue mat, and shift your weight or sit down for short breaks.
- Rolling the sole of your foot over a ball or a frozen water bottle for a few minutes may help ease morning stiffness.
- Keep to a healthy weight to reduce the load on your feet.
- When your heel is sore, swap high-impact exercise such as running for cycling or swimming for a while, rather than stopping exercise altogether.

When to seek medical attention promptly
Seek medical attention promptly if any of the following apply:
- Severe pain, swelling or bruising after a fall or injury to the foot
- Being unable to put weight on the foot
- A hot, red, swollen heel, especially with a fever
- Numbness, tingling or burning spreading through the foot, or weakness in the foot
- Heel pain that keeps getting worse, or is present at rest and at night
Frequently asked questions
Can plantar fasciitis go away on its own?
Many cases settle within a year, but some take longer, and the pain often comes back if the causes aren't addressed. An assessment and a suitable stretching and footwear plan may help you recover sooner, especially if the pain is affecting your work or walking.
Is a heel spur causing my pain?
Not necessarily. A heel spur is a small bony growth on the heel bone that often shows up on X-rays, but many people with spurs have no pain, and many people with plantar fasciitis have no spur. Treatment is usually the same either way.
What shoes should I wear?
Shoes with a cushioned heel, good arch support and a firm heel counter are usually best. While your heel is sore, avoid flat, thin-soled shoes and walking barefoot on hard floors. Insoles or custom orthotics may help some people.
Do I need an injection or surgery?
Usually not. Most cases improve with stretching, footwear changes and other non-surgical treatment. A steroid injection may ease pain in the short term, but it is not usually the first choice. Surgery is generally considered only if severe pain persists after 6 to 12 months of non-surgical treatment.
How many sessions will I need?
It depends on how severe your symptoms are, how long you have had them, and whether other areas such as the calf or lower back are involved. Dr. Ho will discuss an expected treatment plan with you after your first examination.
Will the Voluntary Health Insurance Scheme (VHIS) cover plantar fasciitis treatment?
That depends on your policy terms. Cover for outpatient care, injections, surgery and chiropractic treatment varies between policies, so check with your insurer before your visit. We are happy to provide receipts to support your claim.
Disclaimer
This page is general information only, not a diagnosis or treatment advice. If you have any symptoms, please consult a qualified healthcare professional.